

If soreness now lingers longer than it used to, the usual explanation is that exercise recovery after 50 slows down. Research has not established that. Nor has it established the opposite: one 2025 pooled analysis saw no greater loss of muscle function and less soreness in the older groups, in small studies, mostly of men, that set their own age groups.
So there is no clear case for overhauling your training. Keep your strength work, give hard sessions room, get the recommended sleep, eat enough protein, and learn to tell soreness from injury. Nothing here promises faster recovery, and results vary.
This post is for adults who already train. If you have chronic conditions or symptoms, the Physical Activity Guidelines for Americans say to be under the care of a health care provider, who can advise on the types and amounts of activity that suit you.
Key takeaways
- Slower recovery after 50 is not established. Neither is the reverse.
- Keep your strength work. Spacing hard sessions is a matter of judgment.
- Sleep and protein have published recommendations; neither is shown to change recovery.
- Soreness that builds after a session and fades is expected. Sudden, severe pain is not.
Does recovery really slow down after 50?
Research has not shown that it does, or that it does not. A 2025 meta-analysis (a study that pools earlier studies) of 36 small studies compared 390 older with 389 younger adults. It found no difference in loss of muscle function (strength or power tests) in the 72 hours after one exercise session, and the older groups reported less soreness. Each study set its own age groups, and most included men only. Results for muscle function varied widely between studies.
Not every study agrees. A 2023 scoping review of 27 studies in adults 65 and older found inconsistent results, and its authors called the rate of recovery in older adults unclear. In one small 2010 study of a 55-km trail race, 13 well-trained masters runners (older competitors, average age about 46) had similar muscle damage to 10 younger runners but recovered more slowly.
Among the studies we reviewed, almost none look specifically at ages 50 to 64. In one small 2018 cycling study, nine well-trained masters cyclists (average age about 56) and eight young cyclists recovered physically at similar rates after an interval session, but the masters cyclists reported more fatigue. The 2023 scoping review notes that data in women are lacking compared with men. So what you feel is real, but research cannot yet say that age is the cause.
What is worth changing in your training week?
Two things: keep the strength work, and use judgment on spacing.
Should you cut back on strength work?
Not because of age alone. The Physical Activity Guidelines for Americans recommend muscle-strengthening activities (resistance exercise, such as lifting weights) that involve all major muscle groups on 2 or more days a week for adults.
Aging is associated with losses of muscle mass, strength and function, and a 2019 position statement from the National Strength and Conditioning Association describes resistance training as a way to counter them. A physical therapist or qualified trainer can fit the program to you.
Should you leave more time between hard sessions?
That is a matter of judgment. The Physical Activity Guidelines for Americans summary sets no rest period between strength sessions, and we found none in the other guideline documents we read, so we give no number.
A practical check (our suggestion, not a research finding). Before a hard session, notice whether the muscles you worked hardest last time are still sore. If they are, you might make the day easier, train a different area, or move the session later. Soreness is a rough guide only: in the studies above it did not always match measured recovery. This is for ordinary soreness, not injury pain.
Do sleep and protein change how you recover?
Sleep and protein have published recommendations, but neither is shown to change recovery.
How much does sleep matter for recovery?
Meet the recommended hours for general health; whether that helps recovery from training is thinly studied. The CDC recommends 7 or more hours of sleep a day for adults aged 18 to 60, 7 to 9 hours for ages 61 to 64, and 7 to 8 hours for adults 65 and older.
In one small 2020 trial in 10 young men, going 48 hours without sleep after muscle-damaging exercise did not delay the return of strength. A 2025 systematic review of 13 studies in healthy adults found mixed results for sleep loss and strength performance. We found no study of sleep and recovery from training in adults over 50.
Do you need more protein after 50?
That is debated. The Recommended Dietary Allowance for protein, set by the National Academies, is 0.8 grams per kilogram of body weight a day for adults. Some expert groups, including a European study group writing about people older than 65, argue that older adults need more than the allowance; a 2023 protein review calls the question still debated. For the general population, the 2025–2030 Dietary Guidelines for Americans set a protein goal higher than the allowance.
Trials are mixed. A 2018 meta-analysis of 36 studies in older adults who were not frail found that protein supplements did not increase lean body mass (muscle and other non-fat tissue), muscle strength or physical performance. A 2022 meta-analysis of 74 trials in healthy adults found small additional gains in lean mass and lower-body strength with more protein, mostly alongside resistance exercise. Neither measured recovery between sessions.
People with chronic kidney disease may need to adjust how much protein they eat and should work with a dietitian or their health care professional, according to the National Institute of Diabetes and Digestive and Kidney Diseases. A physician or dietitian can advise on what fits you.
How do you tell normal soreness from an injury?
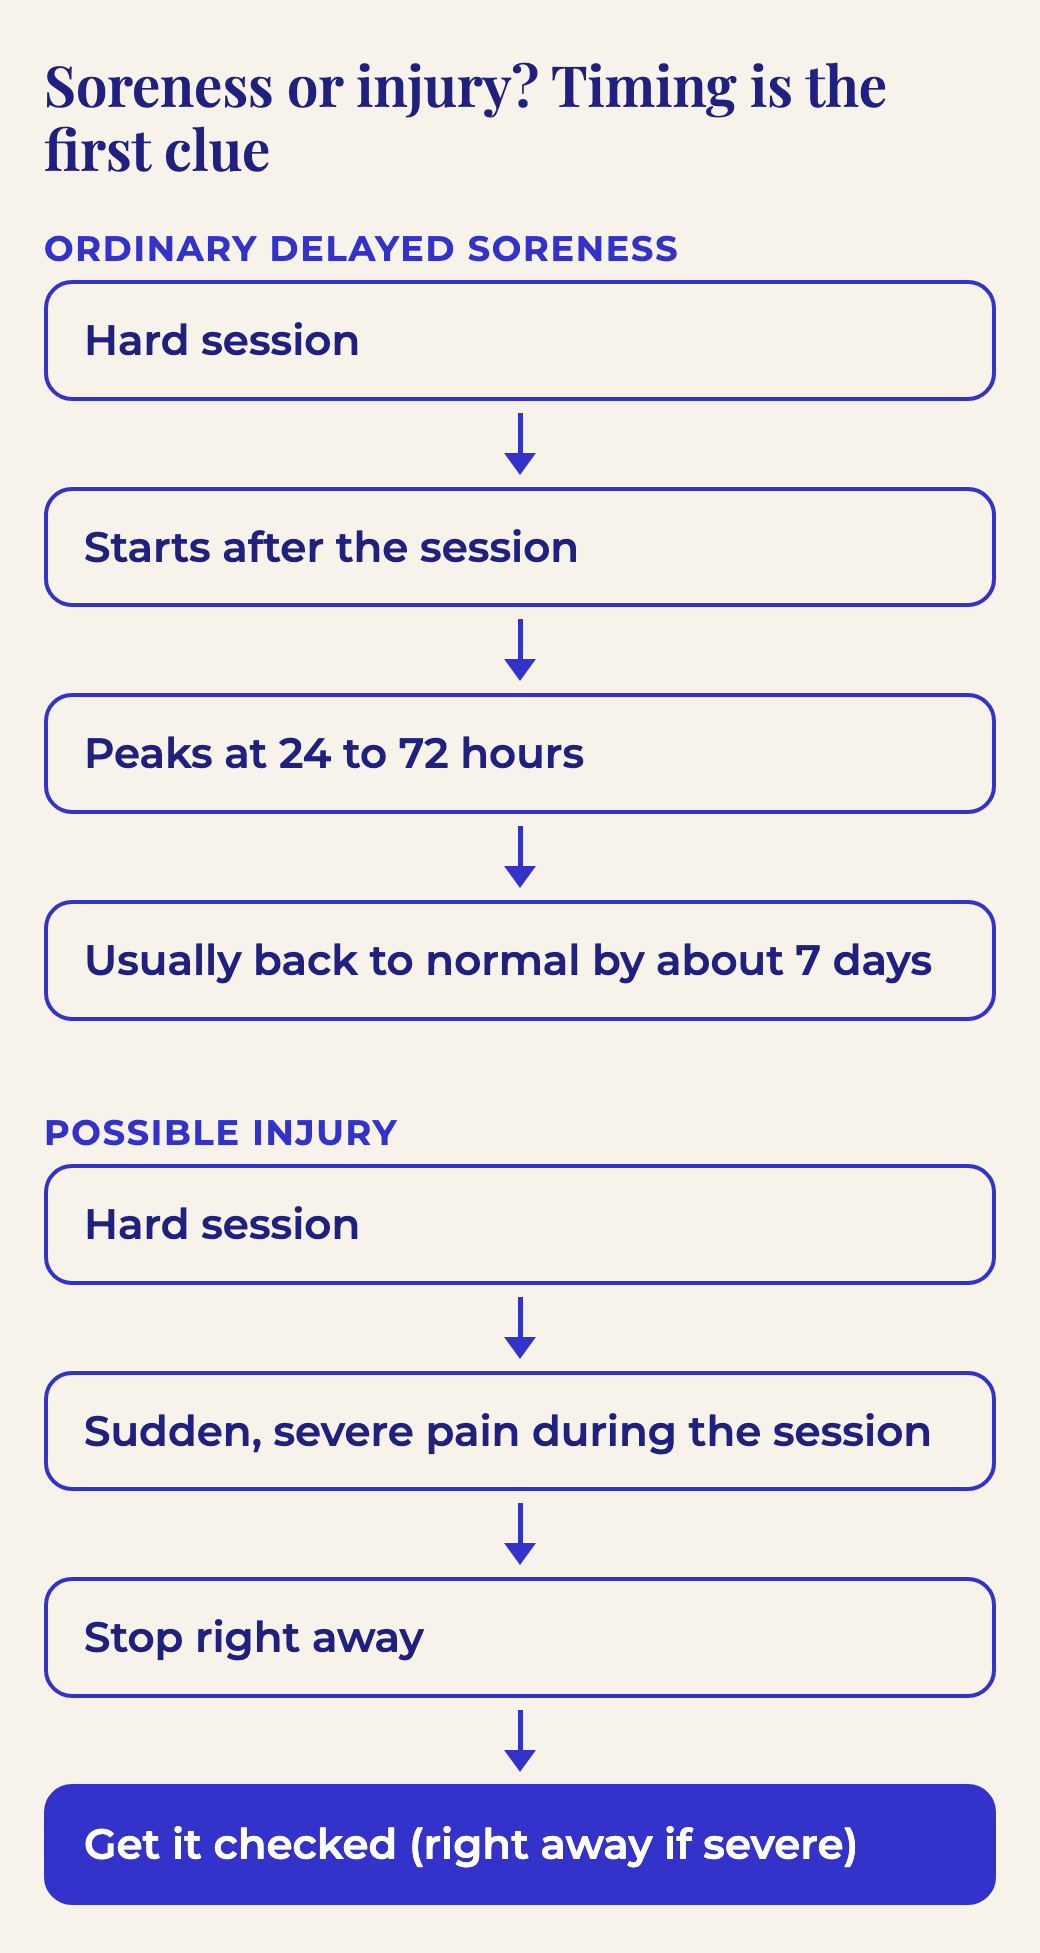
Timing is your first guide. Delayed-onset muscle soreness comes on after exercise your muscles are not used to, rather than during it. It peaks one to three days after the session: a 2018 soreness review says 48 to 72 hours, the 2025 meta-analysis 24 to 48. The meta-analysis describes symptoms as typically recovered by 7 days.
An injury behaves differently. The National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIAMS) lists symptoms of an acute (sudden) sports injury, including:
- sudden, severe pain
- extreme swelling or bruising
- not being able to put weight on a leg, knee, ankle or foot
- not being able to move a joint normally
NIAMS describes chronic (overuse) injuries differently: pain during play or exercise, and swelling and a dull ache at rest.
NIAMS advises stopping right away when a movement or activity causes pain, and not trying to work through the pain of an injury, acute or overuse. It says to check with a health care provider if pain or other symptoms persist.
Ordinary soreness begins after the session, peaks, then eases; the sign NIAMS lists is pain and swelling that do not go away after a few days. This describes patterns; it cannot diagnose you.
What if soreness or an old injury keeps limiting your training?
Then the question is what is causing it. The realistic options:
- A physician’s evaluation, which may include an examination and imaging.
- Physical therapy or a structured exercise program. For knee or hip osteoarthritis, a guideline from the American College of Rheumatology and the Arthritis Foundation strongly recommends exercise.
- Image-guided injections, including cortisone (steroid) injections and platelet-rich plasma (PRP, made from your own blood). The American Academy of Orthopaedic Surgeons notes that the evidence for PRP varies by condition and that more research is needed. Injections carry risks, such as soreness at the site, infection, bleeding or nerve injury (MedlinePlus lists these for steroid injections), and may not help.
- Surgery, which is sometimes necessary, sometimes uncertain and sometimes not the best choice.
What Gramercy Center offers
This section describes Gramercy’s services, not research evidence.
Gramercy Center offers ultrasound-guided platelet-rich plasma (PRP) and bone marrow aspirate (BMA), along with other image-guided injections and procedures. It is a cash-pay, concierge, physician-led practice in Beverly Hills, founded and led by Dr. Preet Patel, MD, and clients always see an MD specialist.
PRP and BMA (concentrated from your own bone marrow) are office-based, for joints, muscles, tendons and nerves, with consultation and treatment possible in a single visit. Not everyone is a candidate, and results vary. The treatments list and the knee pain and shoulder pain pages have details.
When should you stop and see a physician, and when is it an emergency?
Ordinary soreness needs neither. The signs below are sorted by how fast to act.
See a physician for any of these
- pain and swelling that do not go away after a few days (NIAMS)
- pain or other symptoms that persist after a minor injury (NIAMS)
- any sign of infection, such as swelling or redness around the tender muscle (MedlinePlus)
Get medical care right away
- muscle cramps, aches or pains that are more severe than expected, or dark, tea- or cola-colored urine. These are symptoms of rhabdomyolysis (a breakdown of muscle), which MedlinePlus says can follow severe exertion. The CDC says to seek medical attention immediately for any of them; they may not begin until hours or days after the muscle injury.
- after an injury: severe or worsening pain, swelling or bruising, or being unable to put any weight on the area. The UK’s National Health Service (NHS) classes these as urgent, and NIAMS lists severe pain, swelling or bruising and being unable to bear weight as symptoms of a serious injury. After a major fall or accident, use the emergency line below.
Emergency: call 911 or go to the nearest emergency room
- after an injury: you heard a crack; the injured part has changed shape or points at an odd angle; it is numb or tingling; or the skin looks blue or gray or feels cold (emergency signs at the NHS)
- muscle aches with a high fever or a very stiff neck (MedlinePlus says to call 911)
- at any time, including during or after exercise: chest pain, heaviness or discomfort; pain or discomfort in the arms, back, shoulders, neck or jaw; shortness of breath; or light-headedness or sudden dizziness. The National Heart, Lung, and Blood Institute lists these among heart attack symptoms and says to call 911 even if you are not sure.
If you have loss of bladder or bowel control, numbness in the groin or saddle area, sudden or worsening weakness, fever with back pain, pain after a major fall or accident, chest pain, or a sudden, severe headache, call 911 or go to the nearest emergency room right away.

What is the most useful next step?
This week: keep your strength sessions, and use the soreness check as one guide to spacing.
Whether recovery slows after 50 is not established either way; the studies we reviewed include few women and few people in their 50s. If pain or other symptoms persist, have them evaluated; for a sign from the lists above, follow that list.
Schedule a consultation with Dr. Preet Patel.
Sources
Recovery research and training guidance
- Advancing Age Is Not Associated With Greater Exercise-Induced Muscle Damage: A Systematic Review, Meta-Analysis, and Meta-Regression. Journal of Aging and Physical Activity. 2025. https://doi.org/10.1123/japa.2024-0165
- Physical Activity Guidelines for Americans, 2nd edition: Executive Summary. U.S. Department of Health and Human Services. 2018. https://odphp.health.gov/sites/default/files/2019-10/PAG_ExecutiveSummary.pdf
- Recovery from Resistance Exercise in Older Adults: A Systematic Scoping Review. Sports Medicine – Open. 2023. https://doi.org/10.1186/s40798-023-00597-1
- Effects of a trail running competition on muscular performance and efficiency in well-trained young and master athletes. European Journal of Applied Physiology. 2010. https://doi.org/10.1007/s00421-010-1597-1
- Age-related changes in physical and perceptual markers of recovery following high-intensity interval cycle exercise. Experimental Aging Research. 2018. https://doi.org/10.1080/0361073X.2018.1477361
- Resistance Training for Older Adults: Position Statement From the National Strength and Conditioning Association. Journal of Strength and Conditioning Research. 2019. https://doi.org/10.1519/JSC.0000000000003230
Sleep and protein
- About Sleep. Centers for Disease Control and Prevention. 2024. https://www.cdc.gov/sleep/about/index.html
- Effects of Sleep Deprivation on Acute Skeletal Muscle Recovery after Exercise. Medicine and Science in Sports and Exercise. 2020. https://doi.org/10.1249/MSS.0000000000002137
- Implications of sleep loss or sleep deprivation on muscle strength: a systematic review. Sleep and Breathing. 2025. https://doi.org/10.1007/s11325-025-03413-0
- Dietary Reference Intakes for Energy, Carbohydrate, Fiber, Fat, Fatty Acids, Cholesterol, Protein, and Amino Acids. Institute of Medicine, National Academies Press. 2005. https://doi.org/10.17226/10490
- Evidence-based recommendations for optimal dietary protein intake in older people: a position paper from the PROT-AGE Study Group. Journal of the American Medical Directors Association. 2013. https://doi.org/10.1016/j.jamda.2013.05.021
- Dietary protein requirements and recommendations for healthy older adults: a critical narrative review of the scientific evidence. Nutrition Research Reviews. 2023. https://doi.org/10.1017/S0954422421000329
- Dietary Guidelines for Americans, 2025–2030. U.S. Departments of Health and Human Services and Agriculture. 2026. https://cdn.realfood.gov/DGA.pdf
- Effects of protein supplementation on lean body mass, muscle strength, and physical performance in nonfrail community-dwelling older adults: a systematic review and meta-analysis. American Journal of Clinical Nutrition. 2018. https://doi.org/10.1093/ajcn/nqy192
- Systematic review and meta-analysis of protein intake to support muscle mass and function in healthy adults. Journal of Cachexia, Sarcopenia and Muscle. 2022. https://doi.org/10.1002/jcsm.12922
- Healthy Eating for Adults with Chronic Kidney Disease. National Institute of Diabetes and Digestive and Kidney Diseases. 2025. https://www.niddk.nih.gov/health-information/kidney-disease/chronic-kidney-disease-ckd/eating-nutrition
Soreness, injuries and treatment options
- Advances in Delayed-Onset Muscle Soreness (DOMS): Part I: Pathogenesis and Diagnostics. Sportverletzung Sportschaden. 2018. https://doi.org/10.1055/a-0753-1884
- Sports Injuries: Types, Symptoms, & Risk Factors. National Institute of Arthritis and Musculoskeletal and Skin Diseases. 2024. https://www.niams.nih.gov/health-topics/sports-injuries
- Sports Injuries: Diagnosis, Treatment, and Steps to Take. National Institute of Arthritis and Musculoskeletal and Skin Diseases. 2024. https://www.niams.nih.gov/health-topics/sports-injuries/diagnosis-treatment-and-steps-to-take
- 2019 American College of Rheumatology/Arthritis Foundation Guideline for the Management of Osteoarthritis of the Hand, Hip, and Knee. Arthritis & Rheumatology. 2020. https://doi.org/10.1002/art.41142
- Platelet-Rich Plasma (PRP). American Academy of Orthopaedic Surgeons, OrthoInfo. Date not stated on page. https://www.orthoinfo.org/en/treatment/platelet-rich-plasma-prp/
- Steroid injections – tendon, bursa, joint. MedlinePlus Medical Encyclopedia, National Library of Medicine. 2026. https://medlineplus.gov/ency/article/007678.htm
Warning signs
- Muscle aches. MedlinePlus Medical Encyclopedia, National Library of Medicine. 2025. https://medlineplus.gov/ency/article/003178.htm
- Rhabdomyolysis. MedlinePlus Medical Encyclopedia, National Library of Medicine. 2025. https://medlineplus.gov/ency/article/000473.htm
- Signs and Symptoms of Rhabdomyolysis. Centers for Disease Control and Prevention, National Institute for Occupational Safety and Health. 2025. https://www.cdc.gov/niosh/rhabdo/signs-symptoms/index.html
- Sprains and strains. NHS (UK). 2024. https://www.nhs.uk/conditions/sprains-and-strains/
- Heart Attack: Symptoms. National Heart, Lung, and Blood Institute. 2022. https://www.nhlbi.nih.gov/health/heart-attack/symptoms
This content is for general education only and is not medical advice. It does not create a doctor-patient relationship. Treatment decisions should be made with a qualified physician after an individual evaluation. Results vary, and not everyone is a candidate for every treatment.